Robotic-assisted laparoscopic prostatectomy: Kent and Canterbury Hospital
Information for patients from the Urology Department
You have been referred to hospital for a robotic-assisted radical prostatectomy. This leaflet explains the following.
What a robotic-assisted radical prostatectomy is
What the alternatives and risks are
What happens before and during surgery
How to look after yourself following surgery
Who to contact if you have any questions
We hope this leaflet answers some of the questions you may have. If you have any further questions or concerns, please speak to a member of your healthcare team.
What is robotic prostatectomy?
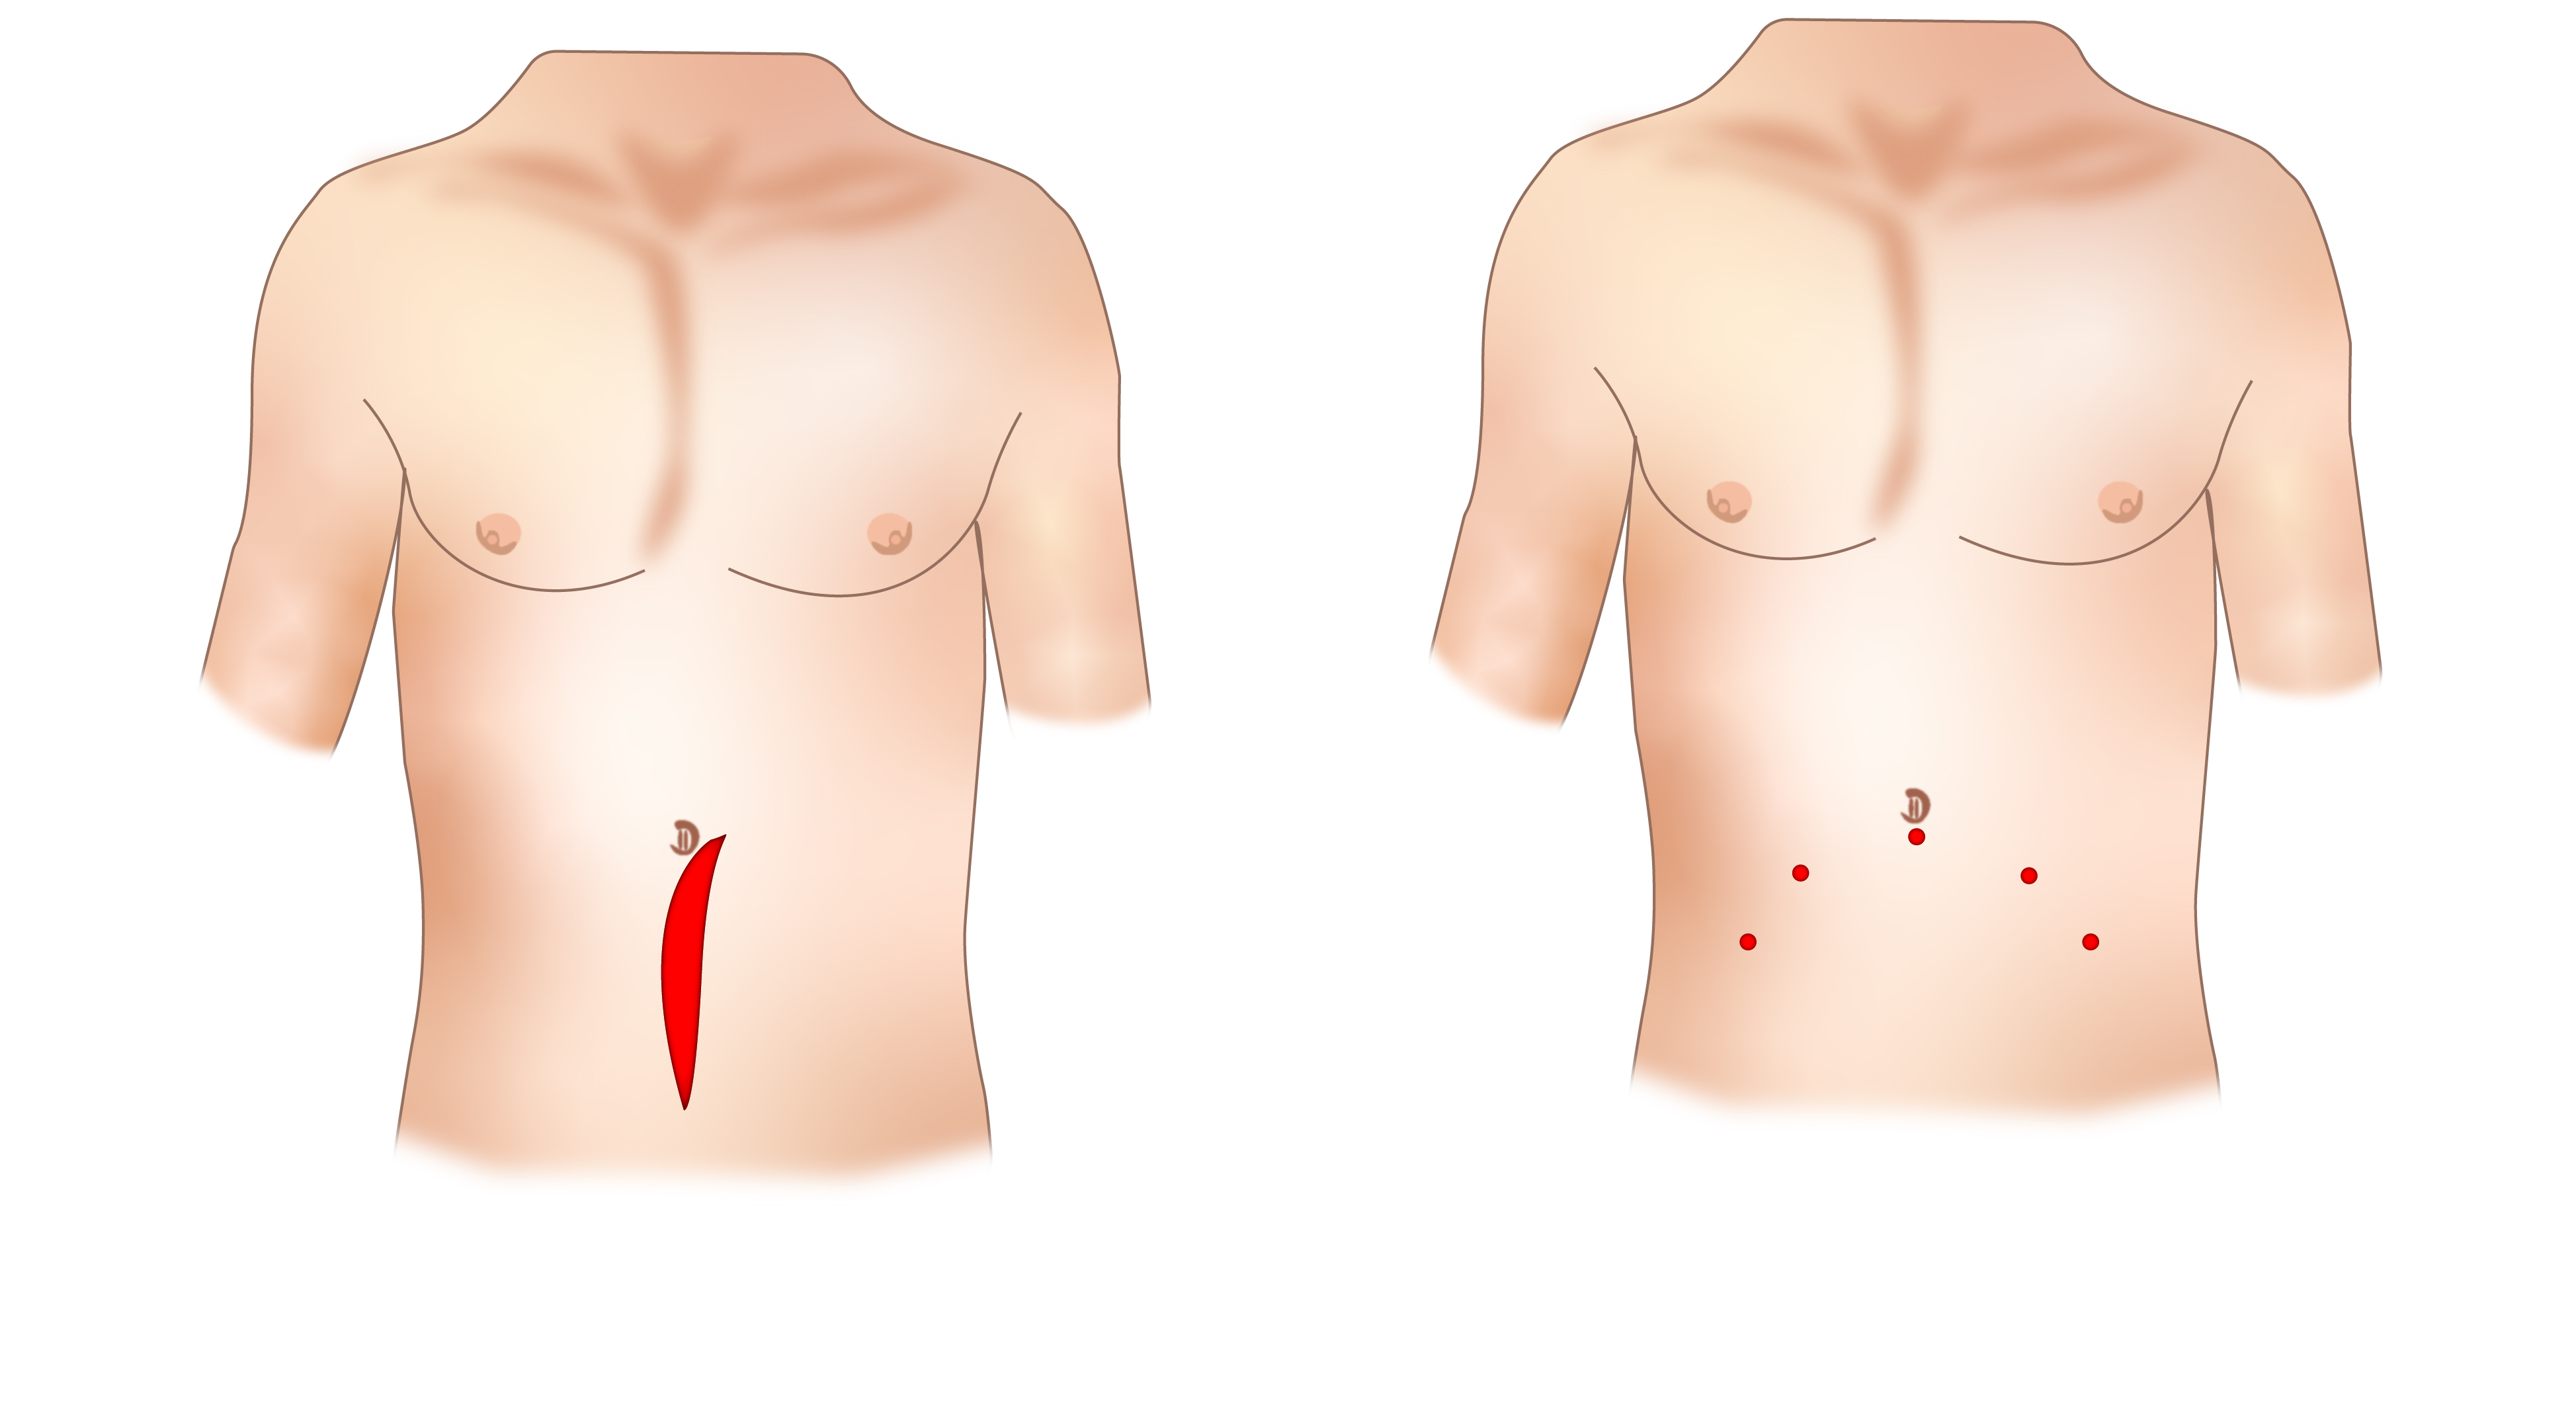
Prostatectomy is the surgical removal of the prostate gland, as a treatment for prostate cancer. To do this surgery, we use a surgical robot called the da Vinci®. The robot enables us to do difficult laparoscopic or keyhole surgery, rather than traditional open surgery.

A surgeon controls the robot at all times. It does not work on its own.
The robot is connected to the patient. Very small instruments are inserted through small surgical incisions (cuts) into the patient’s abdominal wall. The surgeon sits at a separate console and carries out the operation without touching the patient. The surgeon has complete control of the robot at all times.
We are a robotic training centre
We are a training centre in robotic surgery. There may be times when a trainee is operating alongside the consultant under supervision. The trainee:
works under the supervision of consultants at all times
may perform part or all your surgery
Is the surgeon able to do the same operation as an open prostatectomy with the robot?
Yes. For cancer treatment it is regarded as the same as open surgery. Robotic-assisted surgery does not compromise cancer control.
What are the advantages of robotic surgery?
This type of surgery offers many advantages for both you and your surgeon.
Advantages for the surgeon
A magnified high definition view of your operation
A complete 3D view of your prostate when operating
Much finer more delicate dissection
Far more precise surgery
It removes tremor
Advantages for the patient
Lower complication rates
Lower infection rates
Less pain
Quicker recovery
Shorter hospital stay
Shorter catheter time
Less blood loss and a lower rate of needing a blood transfusion
Earlier return to work / normal daily activities
Improved cosmetic result
Are there any alternatives to this treatment?
Yes. You will discuss any alternatives with your urologist or oncologist.
Depending on your age, PSA blood test, type of disease, and other health issues, the following are all treatment options.
Radiotherapy
Brachytherapy
Focal therapy
Surveillance
Hormone therapy
This type of surgery is only chosen if your doctor feels it is the most appropriate treatment option for you, and you are happy to proceed.
Are there any complications to having this surgery?
Yes. All surgery has the potential for complications. However, robotic surgery minimises these risks. You will discuss the risks with your surgeon before signing the consent form.
Short-term risks
Very common risks (affects more than 1 in 10 people)
Bruising in the scrotum and penis, and / or around the wounds. To help avoid this, wear supportive underwear for 2 to 3 weeks following surgery.
Shoulder pain lasting a few hours.
Your face may be swollen for a few hours after surgery. This is due to the head down position you are in during the operation. It is usually mild.
A feeling of abdominal bloating or gas inside the abdomen (stomach). This can last for a few days after discharge. This will settle once your bowels open regularly.
Rectal discomfort or a desire to open the bowels (have a poo). This can last for 1 to 2 hours after your operation.
It is important to avoid constipation. We will give you medication for this. Constipation is when you find it hard to poo.
Urine (pee) may leak down the side of the catheter causing minor leakage. This is called catheter bypassing.
Blood in the urine.
Common risks (affects between 1 in 100 and 1 in 10 people)
Catheter causes bladder spasms / pain.
Urinary or wound infection.
A urine leak is where urine leaks from the join between the bladder and water pipe (urethra). It rarely needs another operation, as it heals on its own over a few days or weeks. Most patients will need their catheter to stay in for longer while the join heals.
You may not be able to completely empty your bladder after we remove the catheter. This is called urinary retention.
Uncommon risks (affects between 1 in 1000 and 1 in 100 people)
Severe bruising across the abdomen. This is rare and settles over the first couple of weeks. Severe bruising does not always mean there is a problem with the operation.
Bleeding that needs a blood transfusion during or after the operation.
Return to the operating theatre or further intervention for complications, such as bleeding.
Damage to structures around the prostate. These include the bowel, rectum, bladder, blood vessels, or ureters. The ureters are the tubes between the kidney and bladder. Injury to the bowel or rectum may need a temporary colostomy to allow for healing. A colostomy is where part of your large bowel (colon) is brought out through an opening made in your tummy. The opening is called a stoma.
Damage to the nerves that supply the muscles in the leg.
Risk of clots in the legs (DVT or deep vein thrombosis), or clots on the lungs (PE or pulmonary embolus). Patients are given injections to reduce this problem. Drinking plenty of fluids and moving around early after surgery, helps prevent this problem.
Medical complications, such as chest infections, heart attack, or stroke.
Re-admission or coming back to hospital for further procedures.
Port site hernias (bowel protruding through wound).
Equipment or technical failure. If this happens, we will cancel or reschedule the operation. If this happens during the operation, we may change from a keyhole to an open operation.
This is major pelvic surgery. As a result there is a risk of death, but this is less than 1 in every 1000 patients.
Rare risks (affects between 1 in 10,000 and 1 in 1000 people)
The surgeon decides to change to an open operation.
Eye problems due to the pressure of the head down position.
Long-term risks
Incontinence (loss of bladder and / or bowel control)
Long-term (longer than a year) incontinence that needs further surgery happens in 2 to 5 in every 100 patients. Most patients will have some incontinence when their catheter is removed. These patients may need to use incontinence pads for a period of time. With robotic surgery, continence recovers quicker.
It is important to do your pelvic floor exercises before, during, and after your recovery. Do not perform them whilst the catheter is first in place, allow any swelling to settle first. For more information, read the Pelvic floor exercises for men undergoing radical prostatectomy leaflet. If needed, we will refer you to the community physiotherapists.
After surgery, you are at higher risk of needing pads long-term, if you already have:
stress urinary incontinence; and / or
urge incontinence.
Some men will become dry within the first week of catheter removal, but most will leak variable amounts of urine (pee). This can often be quite heavy to start with, but improves within 6 weeks.
6 weeks after surgery, 60 to 90 out of every 100 men will be using one pad per day, or they will be dry. If they are still using a pad each day, this will be for intermittent small volume leaks.
Long-term, between 10 and 15 out of every 100 men may need one pad a day. This will depend on how physically active they are.
Approximately 5 in 100 men will need more than one pad per day.
In 3 to 5 in every 100 men, the leakage will cause a problem. The patient will need further corrective surgery, such a male sling or artificial sphincter implant.
It is not unusual for men to use a small “safety pad” for a while, when out and about, mainly for confidence rather than need.
Erectile dysfunction (not able to get or keep an erection that is firm enough for sex)
This surgery will affect erections. This is more likely in older age groups, and if you have weak erections before your surgery.
It may be possible to offer nerve sparing techniques to patients who want to regain their erections. During the prostatectomy, we may be able to protect the nerves that supply the erections. These nerves run very close to the prostate and can be gently peeled off. We do not offer this to patients with more advanced disease. Your surgeon will discuss this with you, if appropriate.
Even with nerve sparing surgery, erections are not guaranteed to recover. We will offer you the following to help with your recovery:
a daily tablet (PDE 5 inhibitor tablet)
the use of a vacuum therapy device, to help improve blood flow to the penis
If spontaneous recovery is going to happen, it can take up to 2 to 3 years.
We have dedicated clinics for erectile dysfunction. We can refer you to these after your surgery, as there are many options available to help. If you want us to refer you, please speak to a member of the team.
Some patients will notice a degree of penile shortening. This is usually between 0.5cm to 2cm of stretched penile length. However, the actual length can vary and some men will experience much greater shortening. This is more common among men who also have erectile dysfunction after surgery.
Urethral / Anastomotic strictures is scar tissue that may form in the water pipe. Around 1 to 4 out of every 100 cases (1 to 4%) will need a procedure called urethral dilatation. Symptoms include a slowing of urinary flow or struggling to pass urine (pee). It can occur soon or many months after the operation.
Cancer outcomes.
If the cancer is confined to the prostate there is a 15 in 100 chance of a positive margin. A positive margin means that there is cancer on the surface of the removed prostate. This suggests that there may be some cancer cells remaining in the body. If the cancer is extending outside the prostate this risk increases to 30 in 100.
Radical prostatectomy to treat prostate cancer does not guarantee that the prostate cancer does not come back. Approximately 1 in 4 patients who have had this procedure will need further treatment. This will be to treat further or recurring disease.
Why has my surgeon suggested I have my lymph nodes removed?
If you have higher grade or higher volume disease, your surgeon may discuss the removal of the lymph nodes in your pelvis. This is to find out if the prostate cancer has spread to these lymph nodes.
Are there any complications to removing the lymph nodes?
A small number of patients may have complications related to the removal of their lymph nodes. These complications can include the following.
Lymphoceles are collections of fluid in the pelvis. They may cause pain or discomfort, and need draining.
A lymph leak is where the lymphatic system produces fluid that needs draining from the abdomen. This needs continued drainage at home.
If lymphoedema or swelling of the leg happens, we refer patients to the Community Lymphoedema team. Lymphoedema can last for 9 to 12 months. In rare cases it is permanent.
Damage to pelvic nerves or blood vessels can affect the nerve on the inner thigh. This can make it difficult to cross your legs.
Pelvic haematomas are a solid swelling of blood in the tissues outside the blood vessels.
Your medical team will find most of these complications before you leave hospital or at your follow-up appointment. If you have any concerns about these risks, please speak to your urologist.
Will I go home with a catheter?
We send most patients home with a catheter in place for 7 to 10 days. We will give you instructions on how to manage your catheter at home.
We will phone you before its removal date, to check on you. If you are happy to remove the catheter yourself at home, we will talk you through how to remove it. We will also give you information about how to do this before we send you home after surgery.
Will I lose my desire / libido after surgery?
This does affect some men in the short-term, due to the stress of diagnosis and treatment. However, long-term the operation should not affect your libido (desire to have sex). It will affect your natural fertility, as you will have no ejaculate following your operation.
When can I have sex again?
Please discuss this with your surgeon. General advice is to wait for 2 to 4 weeks before having sex again.
Can the robot breakdown?
Yes, but this happens in less than 1 in every 200 operations. If the robot does break down:
we will reschedule your operation; or
it can be done as an open operation.
We have had to cancel operations on the day of surgery due to equipment failure when testing before surgery. We rebook affected patients onto the next available surgical list.
What happens now?
The hospital will contact you with a date for your operation.
We will ask you to come to the Pre-assessment Clinic at Kent and Canterbury Hospital. At this appointment, you will have routine bloods tests and an ECG (heart tracing). We will assess your fitness for surgery.
You and your partner will be invited to a ‘Patients Forum’. This group meets once a fortnight or every other Thursday afternoon. They discuss issues surrounding your surgery. Issues can include continence, catheter care, physiotherapy, and erectile function.
On the morning of your operation, go to Clarke Ward at Kent and Canterbury Hospital. You will meet your surgeon, anaesthetist, and nursing staff.
We will ask you to sign the consent form.
Why do I need to sign a consent form?
All patients must give permission before they receive any type of:
medical treatment
test
examination
Consent is usually given when you sign the consent form before your treatment. We may ask you to give your consent verbally (spoken rather than written consent).
You must give your consent voluntarily.
The hospital must give you all the information you need to make a decision about your treatment. This is so you can give us informed consent. Please speak to staff if:
staff have not given you this information; or
they have but you still have questions.
You must be capable of giving consent. This means you understand the information given to you, and can make an informed decision.
When we ask you to give consent, please use this time to ask any questions you may still have. For more information, please go to the NHS Consent for Treatment web page. Remember, you can withdraw your consent for treatment at any time.
How can I prepare for my surgery?
While you wait for your surgery date, you can start preparing for your operation. Research shows that fitter patients, who are able to improve their health and activity levels before surgery, recover more quickly. Taking an active role in planning and preparing for your operation will help you:
feel in control
leave hospital sooner
get back to normal more quickly
To help with this, a member of the One You Kent (OYK) team may contact you. OYK work in the community, and help patients improve their general health. This includes help and advice on the following.
Stopping smoking
Losing weight
Getting more exercise
More information can be found on the following web sites.
One You Kent (Kent Community Health)
Fitter Better Sooner Toolkit (Royal College of Anaesthetists)
How long does the operation take?
The operation takes approximately 2 to 4 hours.
The anaesthetist will give you a general anaesthetic (you are asleep for the operation). They may also give you a spinal injection, so you are more comfortable when you wake up. You will wake up in the recovery bay, before we transfer you back to the ward.
Will I be in pain?
Robotic surgery is less painful than open surgery.
Before you wake up, the anaesthetist will give you pain relief. We also use local anaesthetic (numbing solution) in your wounds and bladder. If you are in pain, please tell the nursing staff so they can give you pain relief.
A lot of patients wake up feeling as though they have a full bladder or get bladder spasms. This is because of the catheter and the surgery around your bladder, not because your bladder is full. This usually settles, but if not, we can give you medication to help.
How long will I be in hospital?
We discharge most patients the day after their operation.
You will wake up after surgery with a catheter, and you may have a drain tube as well. If you have a drain tube, we will remove this before you leave hospital.
How can I help prevent blood clots (DVT or deep vein thrombosis)?
To prevent clots, we may teach you how to give yourself an injection into your stomach. You will need to give yourself this injection each day for 28 days after your surgery. If needed, we will teach you how to do this on the ward before you leave hospital.
We use compression devices during surgery to reduce your risk of developing blood clots. We will also give you surgical stockings to wear for a time after surgery.
Will I have help after I am discharged from hospital?
Yes.
Before leaving hospital, we will give you instructions on how to manage your catheter and wound dressings at home.
You will have dissolvable stitches, so you will not need to have your stitches removed.
We will give you:
laxatives to prevent constipation
injection to reduce your risk of developing blood clots
The following are optional:
tablets to stop gastritis (stomach irritation) for the first week
tablets to help with erection function recovery, which you start once we remove your catheter
If needed, the community nurse is available. You can contact the community nurse via your GP.
The Community Continence team are available and you can ask them for support.
Please call Clarke Ward if you have any problems.
You will find a list of useful contact numbers at the end of this leaflet.
How do I look after myself at home?
Please make sure you have a supply of simple painkillers at home. Simple painkillers include paracetamol and ibuprofen.
Exercise gently to start with. Gradually build up each day, as your symptoms allow.
Do not stay in bed all the time.
Eat a full and balanced high fibre diet and drink plenty of fluids. This is especially important in the first week after your surgery. For more information, read The NHS Eatwell Guide.
Do not drink alcohol for 1 week after your surgery.
Your energy levels can vary from day to day following surgery.
How long will I need a catheter for?
The catheter is a very important part of your recovery. It protects the join between your bladder and your urethra (water pipe) in the early stages of healing. We like to leave the catheter in place for as short a time as possible, between 7 to 10 days after your operation.
Removal of the catheter is very straight forward and only takes a few seconds.
We encourage patients to remove their catheter themselves at home.
This is a very safe and painless procedure. We will demonstrate this at our Prostate Forum, and the ward nurses will also show you before we discharge you home.
Before we discharge you from hospital, we will give you a date to remove your catheter. You will have a telephone appointment for that day. A member of the team will call you before and after you remove your catheter, to make sure it went well.
Your surgeon may decide to leave your catheter in for longer. If this is the case, your surgeon will explain the reasons why.
Once the catheter is removed, please continue doing your pelvic floor exercises regularly.
Remember that to start with, most patients have some leakage once their catheter is removed. You may need to use pads for a period of time. This is where the Kent Continence Service will help you.
When do I get my results?
It takes our pathologists about 4 weeks to process and examine your prostate. You will discuss the results with your surgeon at your follow-up appointment.
Will I need any other treatment?
Most patients do not need any other treatment. However, we may offer radiotherapy to some patients with more advanced disease either:
immediately after their surgery; or
later, if there is a rise in their PSA levels.
We may give other patients a long course of hormones. Your surgeon will discuss this with you. You may need further appointments with your oncologist.
Will I have follow-up appointments?
You will have a follow-up appointment 6 weeks after your surgery. After that, you will have an appointment every 3 months to check your PSA levels. If all is well, we can lengthen the time between your appointments.
You may also have appointments with the physiotherapist to make sure your pelvic floor muscles are recovering. If erectile dysfunction is important to you, we will discuss this with you at a specialist clinic.
When can I drive?
This varies between patients. You will only be fit to drive if you can do an emergency stop without it causing pain. For most patients, this is usually 2 to 4 weeks after surgery.
When can I return to work?
Again this varies between patients. You can return to work when you feel able. Some patients are back to work after 1 week, others take 3 to 4 weeks.
It is important to only do light duties to start with. Do not do any heavy lifting for 6 to 8 weeks.
After robotic surgery, patients return to work quicker. On average they return to work after 3 weeks, compared to 11 weeks after open surgery.
When can I fly?
Do not fly for one month after your surgery. If you have any concerns, please delay your travel. You must check with your carrier and travel insurance company before you travel.
What can we do to improve our service?
We are constantly trying to improve the high quality care we provide. We continually audit and assess our results. We will ask you to fill out questionnaires on your:
continence
erectile dysfunction
overall quality of life
We would like you to fill these out before your operation and at all your follow-up appointments. We also want you to record the first day you manage without pads and when you return to work. Please let us know these dates at your follow-up appointment or by email.
We handle all this information sensitively. Please feel free to add any other comments, whether good or bad. We take all these comments seriously, and use them to improve the experience for future patients.
Where can I get further information about my operation?
East Kent Hospitals. Pelvic floor exercises for men undergoing radical prostatectomy patient leaflet
[Web sites last accessed 28 July 2026]
Useful contact numbers
Clarke Ward, Kent and Canterbury Hospital, Canterbury
Telephone: 01227 783103Kent Community Health Continence Service
Telephone: 0300 123 3167Macmillan Cancer Support
Free helpline: 08088 080000
Practical, financial, and emotional support for people with cancer, their family and friends. Macmillan also has further information on sex, relationships, and cancer.Macmillan Urology Cancer Nurse Specialists
Telephone: 01227 868666
EmailMacmillan Urology Support Workers
Telephone: 01227 868666
EmailProstate Cancer UK
Telephone: 0800 074 8383Sexual Dysfunction Association
Helpline: 08707 743571
For support and information on erectile dysfunction
Ask 3 Questions
There may be choices to make about your healthcare. Before making any decisions, make sure you get the answers to these three questions:
What are my choices?
What is good and bad about each choice?
How do I get support to help me make a decision that is right for me?
Your healthcare team needs you to tell them what is important to you. It’s all about shared decision making.
What do you think of this leaflet?
We welcome feedback, whether positive or negative, as it helps us to improve our care and services.
If you would like to give us feedback about this leaflet, please fill in our short online survey. Either scan the QR code below, or use the web link. We do not record your personal information, unless you provide contact details and would like to talk to us some more.
If you would rather talk to someone instead of filling in a survey, please call the Patient Voice Team.
Patient Voice Team
Telephone: 01227 868605
Email