Flexible sigmoidoscopy and gastroscopy
Information for patients from the Trust's Endoscopy Units
This leaflet is for patients who are having a flexible sigmoidoscopy and a gastroscopy (OGD). It explains what it involves, and any significant risks that there may be.
Please contact the Endoscopy Unit if you cannot come to your appointment. If you do not let us know in advance, we may remove you from the waiting list.
Students and trainees supervised by qualified staff may be involved in your care. If you do not want a student to be present, please tell the endoscopist or nurse-in-charge.
The time on your appointment letter is your booking-in time, not your procedure time. Please tell any friends or relatives coming with you to the hospital.
These tests take 30 to 40 minutes. It may take longer if you have biopsies or polyps removed. Normally you will be able to go home immediately after these procedures. If you have a sedative injection you will need to stay for about 45 minutes. If there are emergencies or very complex cases, we may have to delay the start of your test. You may be in hospital for up to four hours.
What is a gastroscopy?
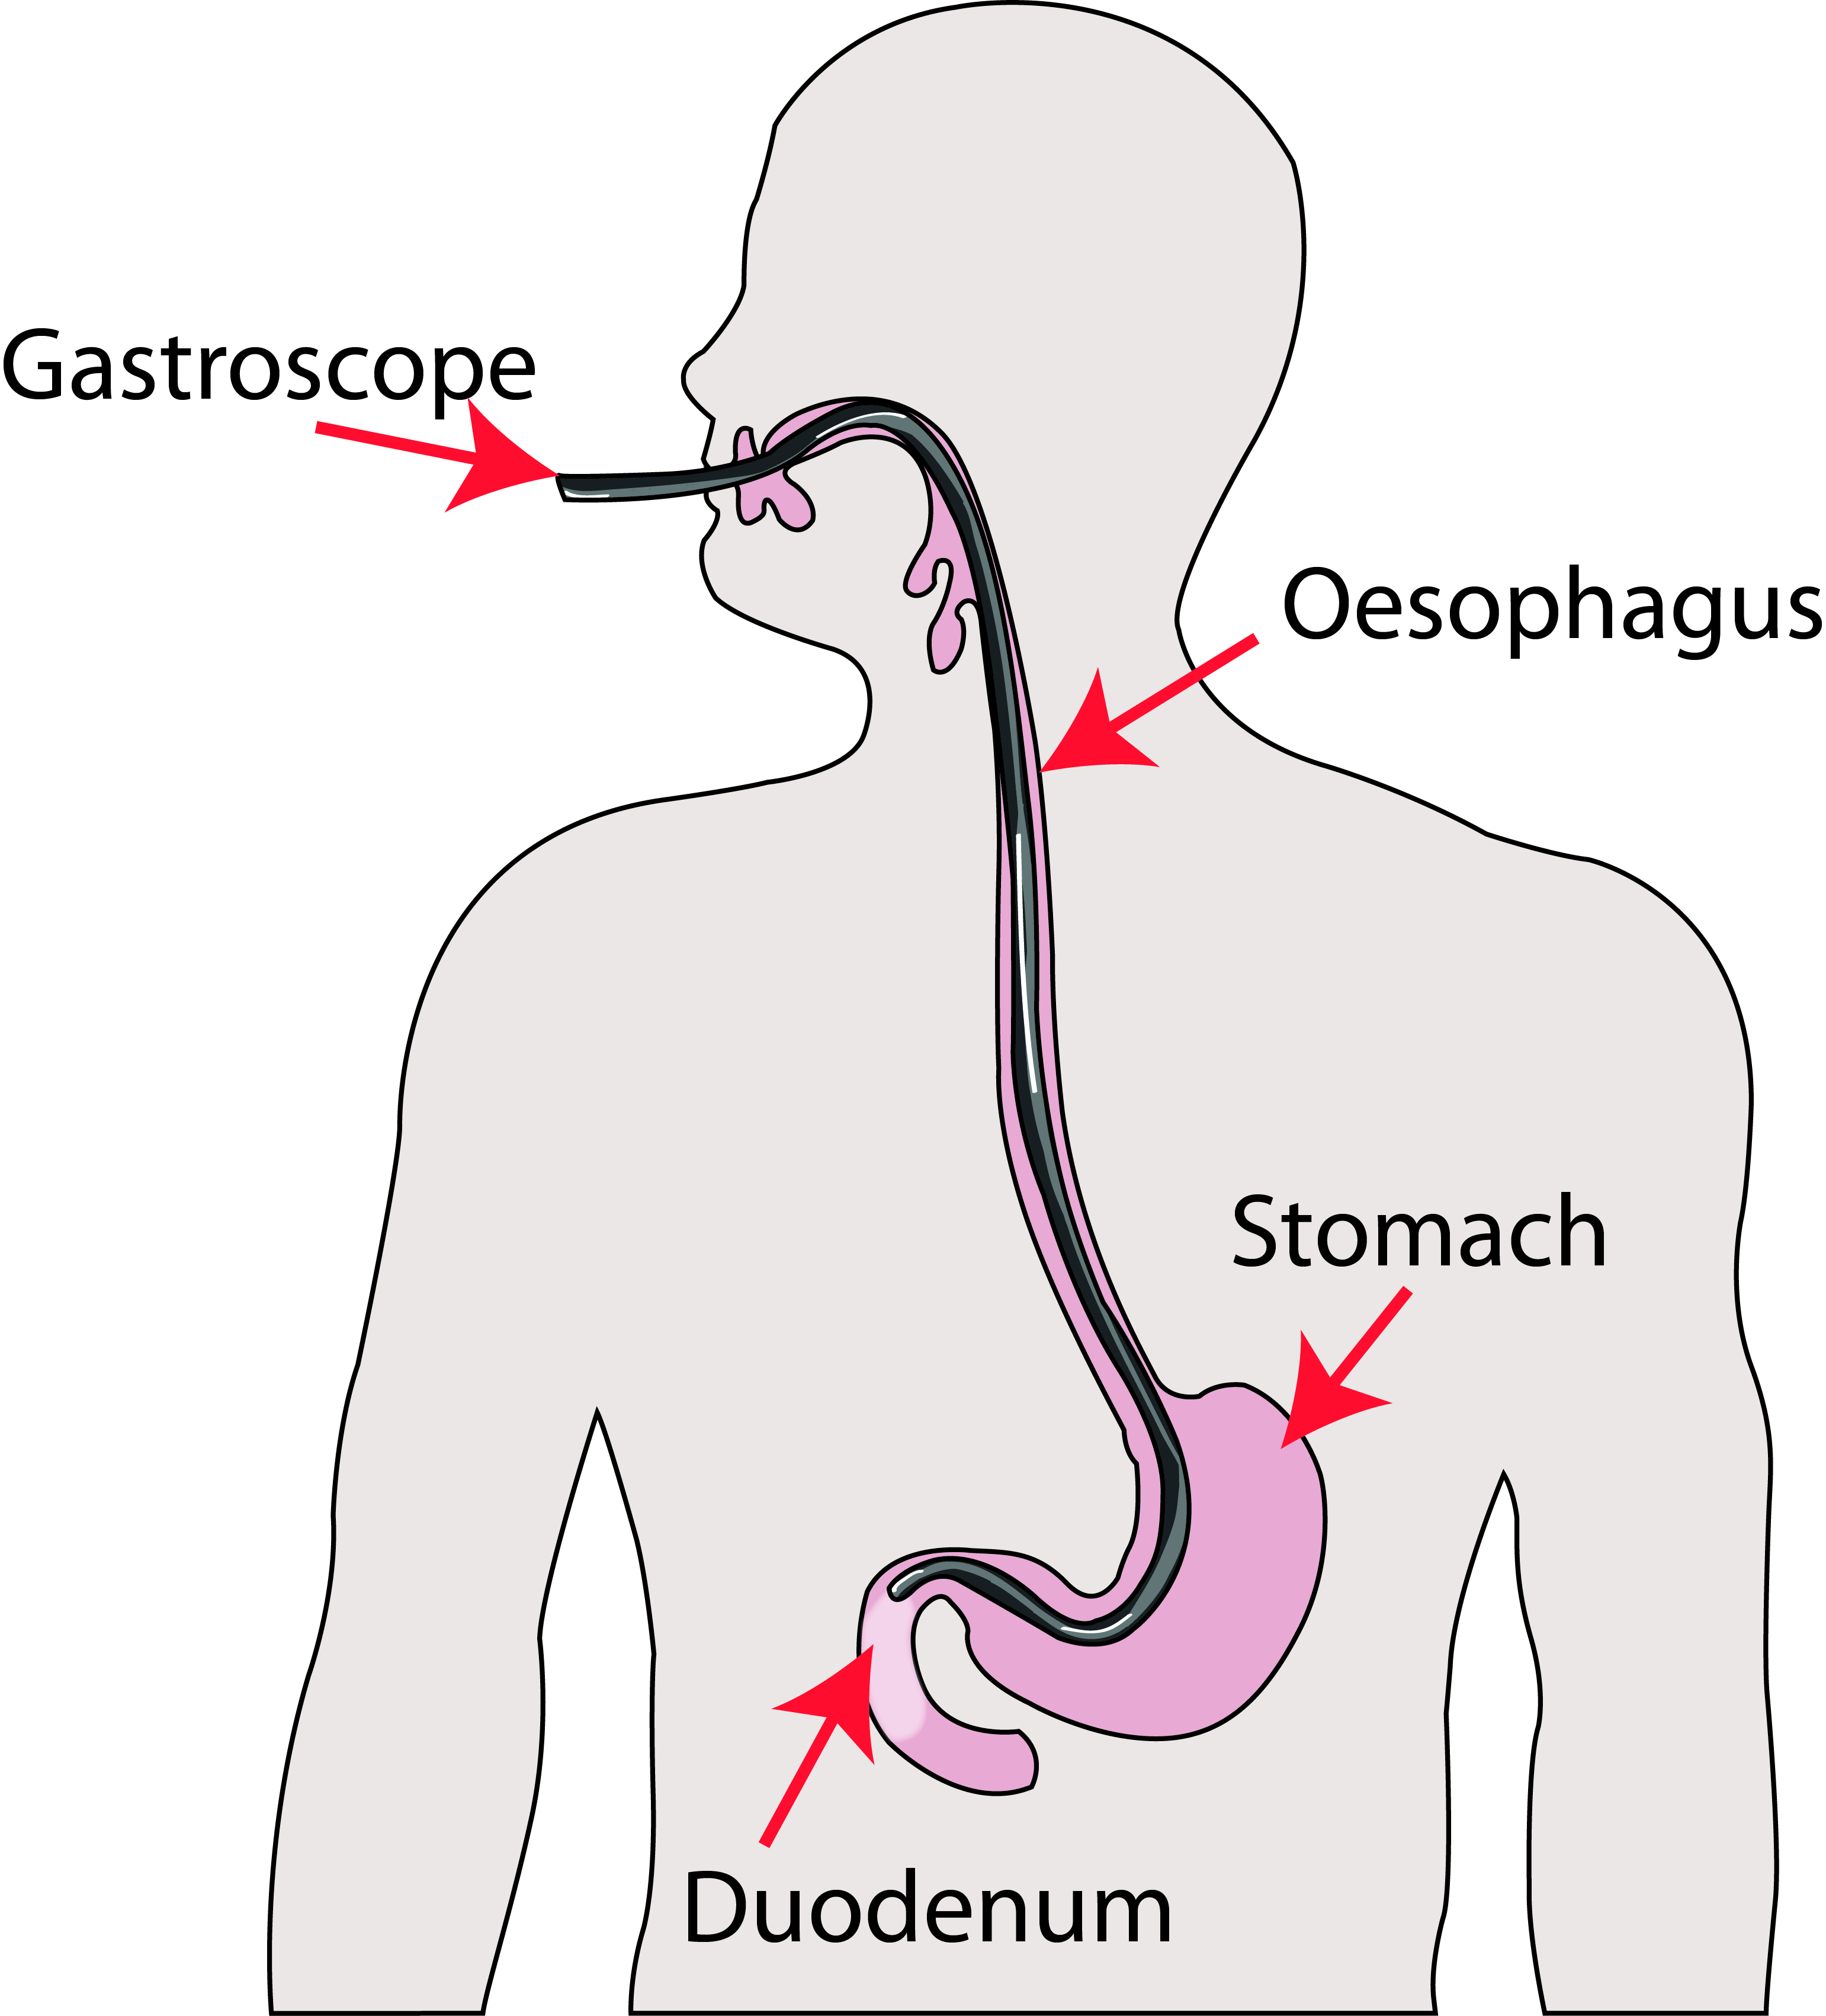
A gastroscopy is an examination of the inside of your:
oesophagus (gullet)
stomach
duodenum (the first bend of the small intestine)
A thin, flexible tube approximately the size of a woman’s little finger (a gastroscope) is passed through your mouth into your stomach. The tip of the gastroscope contains a light and a tiny video camera. This allows the endoscopist to see inside your gut, at what might be causing your symptoms. This procedure is sometimes called an endoscopy.
What is a flexible sigmoidoscopy?

A flexible sigmoidoscopy is an examination, which allows the endoscopist to look directly at the lining of the lower part of your bowel.
This is done using a sigmoidoscope, which is a flexible tube about the thickness of a woman’s index finger. Sometimes a sample (a biopsy) of the lining of your bowel is taken for laboratory examination. If polyps are found they can be removed during the examination.
How do I prepare for my test?
For this test to be successful, your endoscopist must have a clear view of your bowel. Your stomach and bowel must be as empty as possible.
To empty your bowel, you will be given either:
an enema just before your procedure; or
a laxative to take at home before coming into the Endoscopy Unit.
If you have been given medicine to drink to clear your bowels, please follow the instructions enclosed.
You can drink clear fluids up to two hours before your appointment time. Do not drink milk.
Important information for patients taking GLP-1 medication, such as Mounjaro, Wegovy, and Ozempic
Stop eating solid foods for 24 hours before your appointment. Drink clear fluids only (do not drink milk).
If you are to have a phosphate enema, do not eat for six hours before your procedure. Stop drinking two hours before your procedure.
If you are a diabetic or haemophiliac, please phone the Endoscopy Unit for specific advice.
If you have a pacemaker or ICD, please phone the Endoscopy Unit at least one week before your test.
If you have been diagnosed with sleep apnoea and use a CPAP machine, please bring this with you to your appointment and tell the nurse on arrival.
Please remove nail polish and all types of false nails before coming to hospital for your procedure.
Do not bring any valuables to the unit. Please note that East Kent Hospitals accepts no responsibility for the loss or damage to personal property. Unless the property has been handed in to Trust staff for safe-keeping.
Please bring your dressing gown, slippers, and something to read during your stay. Patients feel a spare set of underwear is useful.
Can I continue to take my normal medications?
If you take any of the following medication, phone the Endoscopy Unit at least one week before your test:
warfarin, clopidogrel, dabigatran, rivaroxaban, apixaban, edoxaban, or other blood thinning medications.
Taking certain medications for your stomach, may affect your test results. Unless we have told you otherwise, please stop taking the following medicines seven days before your test.
Cimetidine (Tagamet)
Ranitidine (Zantac)
Nizatidine (Axid)
Lansoprazole (Zoton)
Omeprazole (Losec)
Pantoprazole (Protium)
Rabeprazole (Pariet)
Esomeprazole (Nexium)
Famotidine (Pepcid)
Important: Do not stop these medicines if:
you have been diagnosed with an ulcer
you have Barrett's Oesophagus
you have been specifically advised by your doctor or specialist to continue taking them
If you are unsure whether to stop your medication, please contact the Endoscopy Unit.
You must stop taking the following drugs one week before your test:
iron tablets
stool bulking agents (such as Fybogel, Regulan, and Proctofibre).
Continue to take other medications as normal. Please bring a list of these with you to the Endoscopy Unit.
If you have any queries about your medication, please ring the Endoscopy Unit. It is important to remember to bring any asthma inhalers or angina sprays with you.
Advice for patients taking GLP-1 medications, for example Mounjaro
GLP-1 medications include:
Semaglutides, for example Wegovy, Ozempic, Rybelsus
Tirzepatide (Mounjaro)
Liraglutides
These medications are used to manage diabetes, cardiovascular disease, or weight loss. For patients who take these medications, food moves more slowly through their gut. As a result, if you take these medication you will need to stop eating earlier than other patients, to make sure your stomach is empty of food.
Do not eat food for 24 hours before your appointment. During this time, only drink clear fluids. Do not drink milk.
If you take your GLP-1 medication daily, please take your last dose 24 hours before your procedure.
If you take your GLP-1 medication weekly, please take your last dose one week before your procedure.
What happens when I arrive at the hospital?
Please report to the Endoscopy Unit reception on arrival.
A nurse will check your details, blood pressure, and pulse. If you are allergic to anything (such as medicine, latex, plasters), please tell the nurse.
We will ask you to remove any jewellery, false teeth, glasses, contact lenses, and tongue studs.
Please tell the nurse if you have a pacemaker, replacement joints, pins, or plates.
You will need to change into a hospital gown, and your dressing gown and slippers.
If you have not had a laxative, we will give you an enema to clear your lower bowel completely.
We will explain the procedures to you during your admission. Please do not hesitate to ask any questions you may have. We will ask you to sign a consent form. Remember that you can withdraw your consent for treatment at any time.
A nurse will stay with you throughout your examination.
Why do I need to sign a consent form?
All patients must give permission before they receive any type of medical treatment, test, or examination. Consent is usually given when you sign the consent form before your treatment, but we may ask you to give it verbally.
You must give your consent voluntarily.
The hospital must give you all the information you need to make a decision about your treatment. This is so you can give us informed consent. If you have not been given this information, or you have but you still have questions, please speak to a member of staff.
You must be capable of giving consent. This means that you understand the information given to you and can make an informed decision.
When we ask you to give consent, please use this time to ask any questions you may still have. For more information, please go to the NHS Consent for Treatment web page. Remember that you can withdraw your consent for treatment at any time.
What does the examination involve?
You will not normally have sedation, but occasionally it is used.
If you have sedation, we will insert a small needle into a vein in your hand / arm. We will give you the sedation before starting your examination. This will make you feel relaxed but rarely makes you fall asleep. The needle will be lightly strapped to your hand / arm until you recover from the procedure.
For some patients we offer Entonox when they are having a bowel examination, or no medication at all. Entonox is the pain relief gas that women have while giving birth. It works by taking in a deep breath using a mouth piece.
The nurse or endoscopist will discuss with you whether you will have a local anaesthetic (numbing) spray. We will spray this on the back of your throat. It has a bitter taste.
The endoscopist or nurse will attach a small device to your finger, to record your pulse and breathing. If you have sedation we will give you oxygen.
The nurse will place a cuff on your arm, this tracks your blood pressure if you have sedation. Please tell your nurse if there is a reason why we cannot use a certain arm.
The endoscopist will place a small mouthpiece in your mouth.
The endoscopist will gently insert the gastroscope into your stomach. This is not painful and will not make breathing or swallowing difficult. However, you may feel like retching and feel uncomfortable during your test.
Your stomach will be gently inflated with air to expand it. This is so the endoscopist can see the lining clearly. The air is sucked out at the end of the test.
The nurse may need to clear saliva from your mouth using a small suction tube.
Afterwards the endoscopist removes the gastroscope easily, and the trolley is turned around.
The endoscopist will perform a rectal examination before your sigmoidoscopy.
We will ask you to lie on your left side. Once you are comfortable, the endoscopist will gently insert the sigmoidoscope into your back passage (rectum). The sigmoidoscope is then passed around your large bowel (colon).
Air will be passed into your bowel to expand it. This allows the endoscopist to see your bowel lining more clearly. This may give you some discomfort (sometimes mild pain), but it will not last long.
You may need to pass wind during your procedure, this is normal and the endoscopist is used to it. Please do not be embarrassed.
The endoscopist may take a biopsy (a small sample of the lining of your bowel) during your examination. They will send this to the laboratory for more tests. You cannot feel this. The endoscopist may also take a video recording and / or photographs for your records.
The endoscopist may remove polyps during your examination. You will not feel this either. Polyps are small growths in the lining of the bowel. They are not cancerous, but could turn into a cancer in years to come if we do not remove them.
The endoscopist can remove the polyps during your sigmoidoscopy by cutting them out. They do this by placing a small loop of wire through which a low current of electricity is passed, causing the stem to be burnt through.
Afterwards the endoscopist removes the sigmoidoscope easily.
What happens after my examination?
You will return to the recovery area.
If you had sedation, you will need to rest for about 45 minutes. Once recovered you may eat and drink as normal.
After your procedure you may still have a little wind, but this will pass naturally.
Before you go home the nurse will explain your results to you and any further treatment that is necessary. Any biopsy results will take longer.
We will send a letter to your GP.
Going home
If you had sedation, you must have a friend or relative:
take you home; and
stay with you for at least 24 hours after your procedure.
If you have had sedation, for 24 hours following your test you must not:
drive
drink alcohol
operate machinery, including the oven and kettle
sign important documents
If you have had Entonox you cannot drive for 30 minutes after the last dose.
If you did not have sedation, the restrictions above do not apply.
You may notice that your bowels do not return to normal for a few days following your procedure.
You may have a mild sore throat, but this will pass and is nothing to worry about.
Are there any risks?
These tests are very safe, but there are some risks linked to these procedures.
A reaction to the sedative. The sedative can affect your breathing, making it slow and shallow.
Damage to crowned teeth or dental bridgework.
Fever (raised temperature).
There is a slightly increased risk of developing a chest infection after a gastroscopy.
When a biopsy is taken or a polyp is removed, rarely there may be a little bleeding. This can happen to approximately one in every 100 to 200 examinations where a polyp has been removed. If the bleeding does not stop within 24 hours or is excessive, please contact the Endoscopy Unit or Emergency Department.
A perforation is a little tear in the wall of the bowel. This is rare and can happen to approximately one in every 1000 flexible sigmoidoscopies.
During a gastroscopy the risk of making a perforation is less than one in 9,000.
The risk rises to one in 500 if we find a narrowing or a growth during the procedure.
If we do a balloon stretch to expand the narrowing, the risk rises to one in 50.
We take every care to avoid perforation. If it happens you will need a short stay in hospital and more tests, such as a CT scan. You may need surgery to repair the hole and treatment with antibiotics.
Please talk to your endoscopist before your examination if you have any worries about these risks.
Are there any alternatives to a flexible sigmoidoscopy?
Yes, there is a CT colonoscopy or a barium enema. These procedures need the same kind of bowel preparation as a flexible sigmoidoscopy. However they do not allow the endoscopist to remove polyps or take biopsies. So, if we find abnormalities during these procedures you would probably need a flexible sigmoidoscopy anyway.
Are there any alternatives to a gastroscopy?
Yes, you can have a barium swallow and / or barium meal test, which allows us to get x-ray images of the same areas inside your body. But we get better pictures from a gastroscopy and can take biopsies at the same time. Both of which help with your diagnosis. If we find an abnormality during the barium swallow / meal, you would need a gastroscopy to examine or treat it.
Any further questions?
Please phone the Endoscopy Unit. The units are open Monday to Sunday 8am to 6pm.
Endoscopy Unit, Kent and Canterbury Hospital (K&C), Canterbury
Telephone: 01227 783058Endoscopy Unit, Queen Elizabeth the Queen Mother (QEQM) Hospital, Margate
Telephone: 01843 234370Endoscopy Unit, William Harvey Hospital (WHH), Ashford
Telephone: 01233 616274
If you have any questions between 6pm and 8am Monday to Sunday, please contact the Emergency Department (ED).
ED, Queen Elizabeth the Queen Mother (QEQM) Hospital, Margate
Telephone: 01843 235030ED, William Harvey Hospital (WHH), Ashford
Telephone: 01233 616207
If you develop any severe pain in your neck, chest, or abdomen within the first 24 hours of your procedure, please phone the Emergency Department (see telephone numbers above).
A short film outlining what patients can expect when coming to hospital for an endoscopy is available on the East Kent Hospitals' YouTube channel.
Our units are regularly inspected and audited; please ask if you want any information about our performance standards. You can also visit the Care Opinion web site.
[Web sites last accessed 20 October 2026]
Ask 3 Questions
There may be choices to make about your healthcare. Before making any decisions, make sure you get the answers to these three questions:
What are my choices?
What is good and bad about each choice?
How do I get support to help me make a decision that is right for me?
Your healthcare team needs you to tell them what is important to you. It’s all about shared decision making.
What do you think of this leaflet?
We welcome feedback, whether positive or negative, as it helps us to improve our care and services.
If you would like to give us feedback about this leaflet, please fill in our short online survey. Either scan the QR code below, or use the web link. We do not record your personal information, unless you provide contact details and would like to talk to us some more.
If you would rather talk to someone instead of filling in a survey, please call the Patient Voice Team.
Patient Voice Team
Telephone: 01227 868605
Email