ERCP (Endoscopic Retrograde Cholangio Pancreatography)
Information for patients from the Trust's Endoscopy Units
This leaflet is for patients who are having an ERCP. It explains what is involved and the risks of the procedure.
Please contact the Endoscopy Unit if you cannot come to your appointment. If you do not let us know in advance, we may remove you from the waiting list.
Students and trainees supervised by qualified staff, may be involved in your care. If you do not want students and trainees to be present, please tell the endoscopist or nurse in charge.
The time on your appointment letter is your booking-in time, not your procedure time. Please tell any friends or relatives coming with you to the hospital.
The test takes about 30 minutes. It may take longer if we need to carry out any treatment during the ERCP. If there are emergencies or very complex cases, we may have to delay the start of your test.
What is an ERCP?
An ERCP is a test that allows your doctor to diagnose and treat problems with the tubes (ducts) draining your gallbladder, pancreas, and liver into the upper small intestine (duodenum).
-
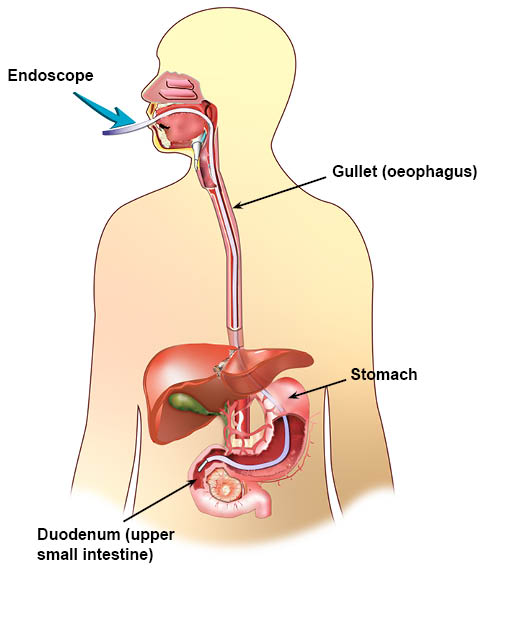 Endoscope passing through the mouth, gullet, stomach, and duodenum
-
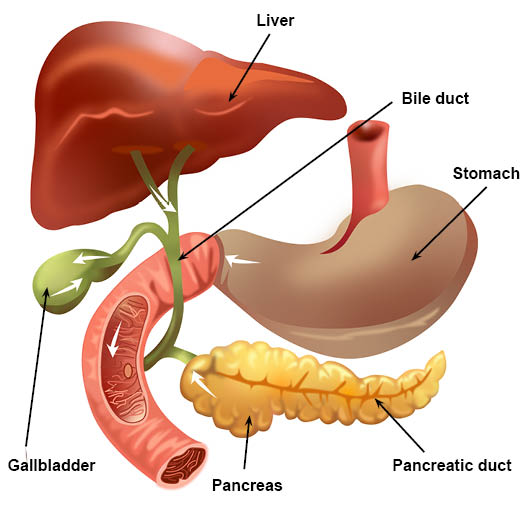 The bile duct and pancreatic duct
To do this test an endoscope is passed through your mouth, via your gullet and stomach, and into the duodenum. An endoscope is a flexible tube about the thickness of a woman’s index finger.
A catheter (a thin plastic tube) is then passed through the endoscope and into the opening of the bile duct, and pancreatic duct if necessary. X-ray dye is gently injected through the catheter. X-ray pictures are taken to check for problems (abnormalities).
How do I prepare for my examination?
Before your ERCP you will need to have a blood test and a further medical assessment, if needed.
Usually you will be asked not to eat for six hours before your procedure. You can only drink clear fluids (such as water) up to two hours before your procedure. Do not drink milk. The Endoscopy Unit will advise you when to begin this period of nil by mouth.
Important information for patients taking GLP-1 medication, such as Mounjaro, Wegovy, and Ozempic.
Stop eating solid foods for 24 hours before your appointment. Drink clear fluids only (do not drink milk).
If you are a diabetic or a haemophiliac, please phone the Endoscopy Unit for specific advice.
If you might be pregnant, please phone the Endoscopy Unit as soon as possible.
Please contact the Endoscopy Unit at least one week before your test, if you are taking:
Warfarin
Clopidogrel
Dabigatran (Pradaxa)
Rivaroxaban (Xarelto)
Apixaban (Eliquis)
Edoxaban (Lixiana)
Ticagrelor (Brilique)
other blood thinning medications
If you have a pacemaker or ICD, please phone the Endoscopy Unit at least one week before your test.
Continue to take other medications as normal. with a sip of water. Please bring a list of them with you to the unit. If you have any queries about your medication, please phone the Endoscopy Unit.
It is especially important to remember to bring any asthma inhalers or angina sprays with you.
If you have been diagnosed with sleep apnoea and use a CPAP machine, please bring this with you to your appointment and tell the nurse on arrival.
Please remove nail polish and all types of false nails before coming to hospital.
Please bring your dressing gown, slippers, and something to read during your stay.
Do not bring any valuables to the unit. East Kent Hospitals accepts no responsibility for the loss or damage to personal property. Unless the patient has handed their property to Trust staff for safekeeping.
Advice for patients taking GLP-1 medications, for example Mounjaro
GLP-1 medications include:
Semaglutides, for example Wegovy, Ozempic, Rybelsus
Tirzepatide (Mounjaro)
Liraglutides
These medications are used to manage diabetes, cardiovascular disease, or weight loss. For patients who take these medications, food moves more slowly through their gut. As a result, if you take these medication you will need to stop eating earlier than other patients, to make sure your stomach is empty of food.
Do not eat food for 24 hours before your appointment. During this time, only drink clear fluids. Do not drink milk.
If you take your GLP-1 medication daily, please take your last dose 24 hours before your procedure.
If you take your GLP-1 medication weekly, please take your last dose one week before your procedure.
What happens when I arrive at the hospital?
Please report to the Endoscopy Unit reception on arrival.
A nurse will check your details, blood pressure, and pulse. If you are allergic to anything (medication, plasters, latex), please tell the nurse.
We will ask you to remove any jewellery, glasses, contact lenses, tongue studs, and false teeth before your examination.
Please tell the nurse if you have a pacemaker, replacement joints, pins, or plates.
To help prevent infection, we may give you antibiotics before your procedure.
We give most patients a painkiller suppository before their procedure, to reduce the risk of pancreatitis (inflammation of the pancreas).
You will have the procedure explained to you during your admission. Please do not hesitate to ask any questions you may have. We will ask you to sign a consent form. Remember that you can withdraw your consent for treatment at any time.
You will need to change into a hospital gown.
A nurse will stay with you throughout your examination.
Why do I need to sign a consent form?
All patients must give permission before they receive any type of medical treatment, test, or examination. Consent is usually given when you sign the consent form before your treatment, but we may ask you to give it verbally.
You must give your consent voluntarily.
The hospital must give you all the information you need to make a decision about your treatment. This is so you can give us informed consent. If you have not been given this information, or you have but you still have questions, please speak to a member of staff.
You must be capable of giving consent. This means that you understand the information given to you and can make an informed decision.
When we ask you to give consent, please use this time to ask any questions you may still have. For more information, please go to the NHS Consent for Treatment web page. Remember that you can withdraw your consent for treatment at any time
What does the examination involve?
We may spray your throat with a local anaesthetic that has a numbing affect. It has a slightly bitter taste.
A small needle will be inserted into a vein in your hand / arm. A sedative and painkiller will be given before your examination to help you feel more relaxed and sleepy. The needle will be left lightly strapped to your hand / arm until you have recovered from the procedure.
We will ask you to lie on your left side with your left arm behind your back, and turned partly onto your stomach. A guard will be placed in your mouth to protect your teeth.
We will attach a small device to your finger to record your pulse and breathing. We will give you oxygen.
A cuff will be placed on your arm to monitor your blood pressure.
Three small ECG pads will be placed on your back, to monitor your heart during the procedure.
Once you are sleepy, the endoscopist will begin the test.
Your stomach and duodenum will be gently inflated with air to expand it. This allows the endoscopist to see the lining more clearly. The air is sucked out at the end of the test.
The nurse may need to clear excess saliva from your mouth using a small suction tube.
If a narrowing is found in your bile duct, the endoscopist will insert a tube (stent) to allow the bile to drain. This may stay in place permanently or be removed at a later date.
If the endoscopist finds a gallstone in your bile duct, they may enlarge the opening of your bile duct with a cut. This is done using an electrical current (diathermy), which the endoscopist will use to remove the stones. If the stone is very large, or if there are a lot of stones, it may not be possible to remove all in one go. In this case, a stent is left in your bile duct and we will arrange a further appointment for you.
The endoscopist may also take a biopsy (a small sample of the lining of your bowel). This will be sent to the laboratory for more tests. You cannot feel this. The endoscopist may take a video recording and / or photographs for your records.
In about one in 15 cases, it will not be possible to treat your problem at ERCP. For example, the opening of your bile duct may be too narrow to allow the catheter to be inserted. If this happens, we will discuss further treatment options with you after your procedure.
What happens after my examination?
You will return to the recovery area to rest.
You may still have a little wind; this is natural.
In some cases we will discharge the patient after a period of observation (up to four hours). If the procedure was complex, or you are at increased risk of complications, you may need to stay in hospital overnight for observation.
You may also be kept nil by mouth for up to 24 hours. Nil by mouth means not eating or drinking. If your procedure was straightforward you can usually eat some light food and drink once:
you are fully awake; and
the local anaesthetic spray in your throat has worn off.
You will be told of the result of your examination. Biopsy results will take about a week to come back.
We will send a letter to your GP.
What happens when I go home?
The decision to allow you to go home will be made after your procedure.
If you had sedation, you must have a friend or relative:
take you home; and
stay with you for at least 24 hours after your procedure.
If you have had sedation, for 24 hours following your test you must not:
drive
drink alcohol
operate machinery, including the oven and kettle
sign important documents
You may have a mild sore throat, but this will pass after a few days.
You may feel a little bloated from any air left in your stomach, again this will pass.
Are there any risks?
ERCP is generally a well-tolerated procedure but there are significant risks.
Damage to crowned teeth or dental bridgework.
Cardiovascular (heart and blood vessels) or respiratory (lung and breathing) complications can happen. This is a result of the sedatives and painkillers you need during your procedure.
Inflammation of the pancreas called pancreatitis, which causes abdominal pain. If this happens, you may need to stay in hospital for a few days for intravenous (IV) fluids and painkillers. On rare occasions, it may be severe and a patient may need to be admitted to Critical Care.
Infection of the bile duct or gallbladder can happen. Although, often ERCP is done to provide drainage of infection.
Bleeding: if a cut is made into your bile duct to remove a gallstone or place a stent, there is a risk of bleeding. The endoscopist can often treat bleeding immediately, or during a later endoscopy procedure. A blood transfusion may be needed. If bleeding is severe, it may need occlusion of the bleeding vessel by a radiologist (usually by accessing groin blood vessels) or surgery.
A perforation is a little tear in the wall of your bowel. This is usually managed with:
intravenous fluids and food
antibiotics
nil by mouth
occasionally, surgical repair
You may have a sore throat after your procedure, but this normally clears up in a few days.
The European Society of Gastroenterology published a guideline of ERCP related adverse events in 2019. The incidence of adverse events was summarised and is shown below.
It is important to realise that the risks listed below are for all patients, including patients who are very sick and might be in Critical Care. In general the severity and outcome of a complication depends on how fit the patient is before they have their ERCP.
ERCP is often the least invasive way to drain bile ducts, remove bile duct stones, and treat sepsis.
The risks include all adverse events from mild to severe, and are approximate. The overall risk of death, attributable at least in part to the ERCP, is one in 200; this includes some very unwell patients undergoing urgent procedures.
Frequency of ERCP related adverse events (ESGE Clinical Guideline, Endoscopy 2019)
Pancreatitis: affects one in 20 patients.
Infection of bile ducts or gall bladder: affects one in 30 patients.
Bleeding: affects one in 30 patients.
Significant perforation: affects one in 300 patients.
Please discuss risks and benefits of the procedure with your endoscopist.
Further information
Please phone the Endoscopy Unit. The Units are open Monday to Sunday 8am to 6pm:
Endoscopy Unit, Kent and Canterbury Hospital (K&C), Canterbury
Telephone: 01227 783058 (not always staffed at weekends)Endoscopy Unit, Queen Elizabeth the Queen Mother (QEQM) Hospital, Margate
Telephone: 01843 234370Endoscopy Unit, William Harvey Hospital (WHH), Ashford
Telephone: 01233 616274
If you need urgent advice following ERCP, between 6pm and 8am Monday to Sunday, please contact the Emergency Department (ED).
ED, Queen Elizabeth the Queen Mother (QEQM) Hospital, Margate
Telephone: 01843 23 50 30ED, William Harvey Hospital (WHH), Ashford
Telephone: 01233 616207
A short film outlining what patients can expect when coming to hospital for an endoscopy is available on the East Kent Hospitals web site.
If you develop any severe pain in the neck, chest, or abdomen within the first 24 hours of your procedure, please phone the Emergency Department (see telephone numbers above). You will be given a leaflet after your ERCP which will give you more details on possible risks when you go home and general advice.
Our Units are regularly inspected and audited; please ask if you want any information about our performance standards. You can also visit the Care Opinion web site.
[Web sites last accessed 20 October 2026]
Ask 3 Questions
There may be choices to make about your healthcare. Before making any decisions, make sure you get the answers to these three questions:
What are my choices?
What is good and bad about each choice?
How do I get support to help me make a decision that is right for me?
Your healthcare team needs you to tell them what is important to you. It’s all about shared decision making.
What do you think of this leaflet?
We welcome feedback, whether positive or negative, as it helps us to improve our care and services.
If you would like to give us feedback about this leaflet, please fill in our short online survey. Either scan the QR code below, or use the web link. We do not record your personal information, unless you provide contact details and would like to talk to us some more.
If you would rather talk to someone instead of filling in a survey, please call the Patient Voice Team.
Patient Voice Team
Telephone: 01227 868605
Email